- Two-thirds of large employers now cover GLP-1s for weight loss, but Business Group on Health data shows that share is expected to decline in 2027 as costs mount.
- Coverage alone doesn't solve the underlying problem: Prime Therapeutics research found only 8% of people who start a GLP-1 for weight loss are still taking it three years later.
- EBRI simulation modeling estimates that expanding GLP-1 coverage can raise employer costs by roughly 5% to 14% a year, depending on eligibility rules and adherence.
- The real decision in front of employers isn't whether GLP-1s are covered. It's whether weight is being managed as an ongoing condition or a single prescription.
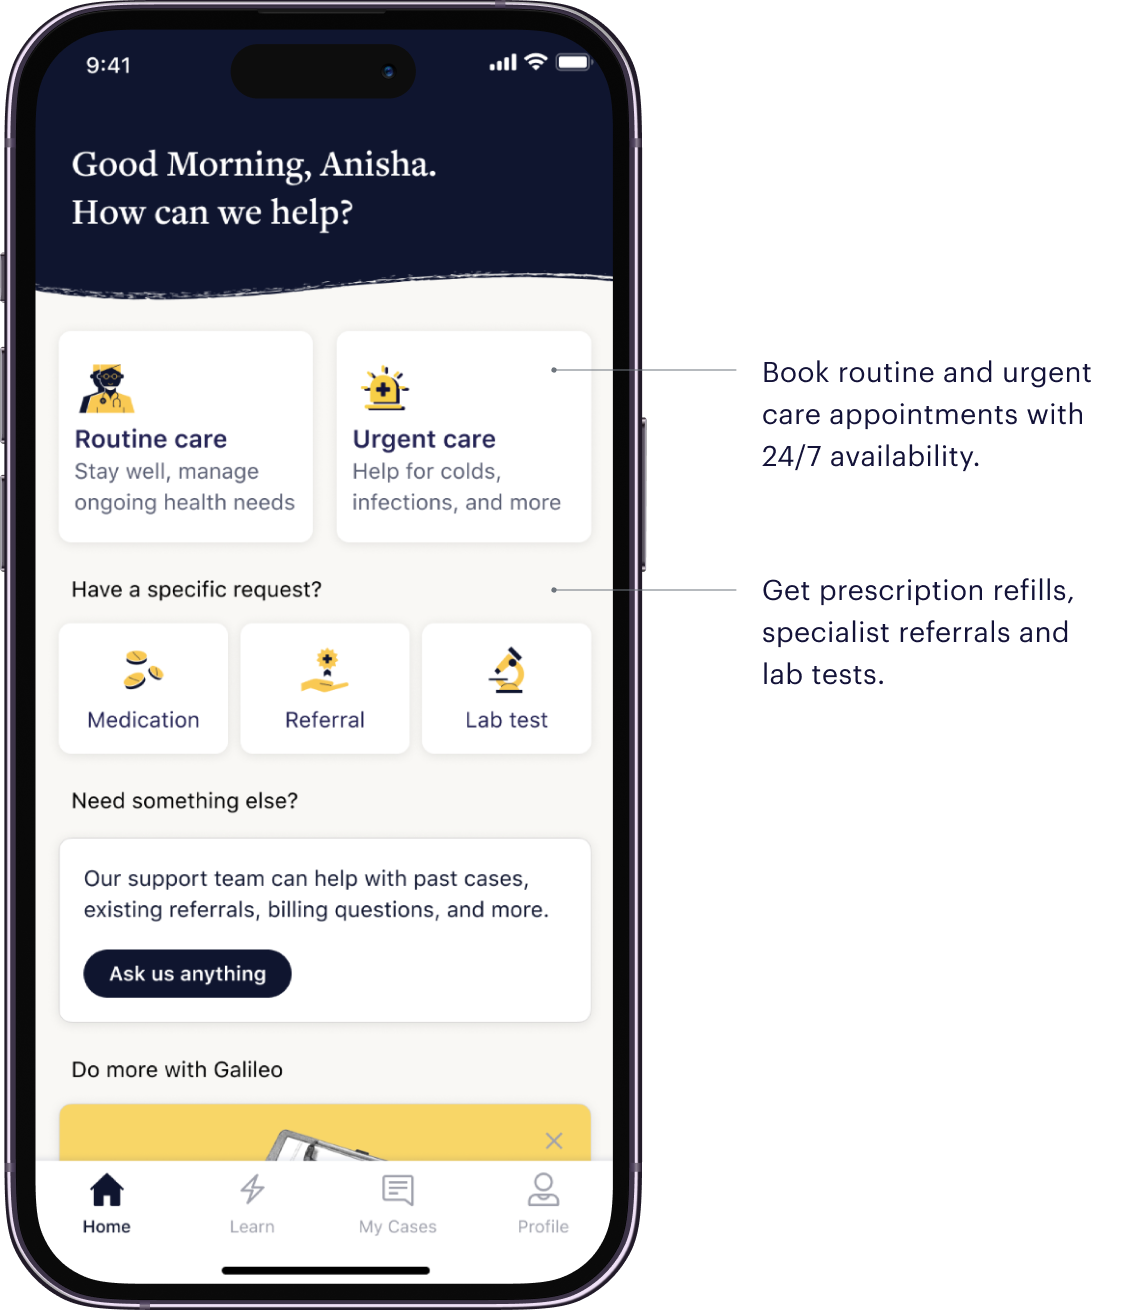
- Galileo treats weight management as a core function of Advanced Primary Care, not a drug benefit layered onto a fragmented plan.
A GLP-1 program for employers usually starts with a coverage question: do we add it, exclude it, or restrict it to a diagnosis? Every renewal cycle makes that question more expensive to get wrong, but it is also the wrong starting point. Coverage determines who can access a medication. It says nothing about whether that drug is being used as part of an actual employer health care strategy, or whether an employer is picking up a growing pharmacy bill for a treatment that, on its own, rarely produces a lasting result.
Excess weight is a chronic condition, and that's the premise Galileo builds from: chronic conditions require continuous, coordinated primary care, not a standalone prescription. A plan that covers the drug but leaves diagnosis, monitoring, and lifestyle support to chance is optimizing for access, not for outcomes. Employers managing this well are not asking, "Should GLP-1s be covered?" They are asking "does our care model actually help people," and coverage is one part of the answer, not the whole answer.
What Employers Should Consider Before Adding GLP-1 Coverage
Before a plan adds or expands coverage, a few questions matter more than the decision itself.
- Is access tied to a clinical pathway, or just a diagnosis code? A plan that approves a GLP-1 medication based on a BMI threshold or a single diagnosis code alone, with no clinical evaluation of candidacy or readiness, is authorizing prescriptions rather than managing a condition.
- Who is monitoring duration and results over time? Without a defined follow-up plan, employers can end up paying for months of therapy after a member has already stopped taking it, or continuing indefinitely with no clear reassessment point.
- Is lifestyle support built in or bolted on? Nutrition counseling, behavioral support, and activity guidance change how well the medication works and how long people stay on it. If that support lives in a separate point solution from the prescriber, members can fall through the gap between them.
- What happens on the other clinical indication? Many employers already cover this class of drug for that condition as standard care. Weight loss coverage needs the same clinical rigor, not weaker oversight.
The Real Cost of a GLP-1 Program for Employers in 2026
Based on Business Group on Health's 2026 survey of large employers, 67% currently include GLP-1s in their weight-loss benefit, and nearly 8 in 10 report that these drugs are driving up their overall health care costs. Utilization has grown alongside coverage: the International Foundation of Employee Benefit Plans found that GLP-1 prescriptions climbed from 6.9% of annual claims in 2023 to 11.4% today.
Mercer's benefits research puts a number on how seriously employers are taking this: 77% say managing this cost is extremely or very important, and list prices for these medications commonly exceed $1,000 a month before rebates. Even with a PBM negotiating net cost down, GLP-1s remain one of the fastest-growing lines in pharmacy spend.
The financial impact is measurable, too. EBRI's simulation-based analysis modeled a range of employer scenarios and found that expanding coverage can raise premium costs anywhere from about 5% to nearly 14% a year, depending on drug pricing, cost-sharing structure, and how broadly eligibility is defined. That range alone explains why so many benefits leaders now treat GLP-1s as their own line item rather than folding them quietly into general pharmacy trend.
Why GLP-1 Coverage Alone Doesn't Solve the Problem
Here is the piece that gets lost in coverage debates: most people who start a GLP-1 drug for weight loss do not stay on it long enough to sustain the result.
Prime Therapeutics' most recent persistence research, published in January 2026, followed members without diabetes who started a GLP-1 for weight loss. Only 8%, roughly 1 in 12, were still taking it at three years. Even among people using higher-potency, weekly-dosed drugs like Wegovy, three-year persistence was just 14%.
That gap between prescribing and lasting results is exactly why coverage alone is a weak strategy. When people stop taking these drugs, the evidence is consistent that much of the lost weight returns. An employer that expands access without a plan for monitoring, follow-up, and lifestyle support is effectively funding a high-cost benefit with no mechanism for improving the odds that it works.
How Employers Should Think Beyond GLP-1 Coverage Toward Comprehensive Obesity Management
The employers getting better results treat excess weight the way they would treat any other chronic condition: something that needs ongoing clinical management. In a coverage-only model, the PBM approves the prescription, and no one is accountable for whether it actually leads to improved health.
In a primary-care-led model, a clinical team evaluates candidacy, prescribes when appropriate, monitors labs and vital signs over time, and adjusts the plan, including lifestyle changes and behavioral support, based on how the member is actually doing.
This is where Galileo's approach differs from most vendors in this space. We manage it as part of Advanced Primary Care: the same clinical team that evaluates a member's candidacy for this medication also manages their type 2 diabetes, their blood pressure, and their behavioral health, because those conditions are rarely separate in practice.
A care model that treats weight, other cardiometabolic risks, and mental health as three, disconnected point solutions will consistently underperform one that treats them as a single person's health.
What a Corporate Weight Management Program Should Include
A workplace weight loss program built around durable outcomes, not just drug access, generally includes the following:
- Clinical evaluation for candidacy: A licensed clinician reviews a member's full health history, not just a BMI number, before starting the medication.
- Integrated cardiometabolic care: Weight, metabolic markers, and cardiovascular risk are managed together, since they are clinically connected.
- Structured lifestyle support: Nutrition guidance, behavioral coaching, and activity recommendations run alongside treatment, not as an optional add-on members have to seek out separately.
- A defined monitoring and duration plan: Regular follow-up visits track progress, manage side effects, and determine when to continue, adjust, or discontinue therapy.
- A single point of clinical accountability: One care team, not a prescriber, a separate coaching app, and a disconnected benefit, owns the outcome.
This is the model Galileo's clinical teams run for employer populations: one team handling candidacy, prescribing, monitoring, and lifestyle support, instead of a prescription handed off to a member with no coordinated follow-up.
How to Manage GLP-1 Costs Without Cutting Coverage
Cutting access outright tends to backfire: it pushes employees toward direct-to-consumer platforms or compounded alternatives the employer has no visibility into, without actually reducing demand. A more durable approach focuses on how the benefit is managed, not just whether it exists.
- Tie eligibility to clinical evaluation, not a blanket diagnosis code: Authorization criteria built around a real clinical assessment reduces spend on members unlikely to benefit, without denying access to those who will.
- Negotiate PBM terms specifically for this drug class: Net cost varies significantly by contract; employers who go into renewal with claims data already organized tend to secure better rebate terms than those who wait for the carrier's rate increase.
- Pair the medication with a lifestyle program: Members who receive structured nutrition and behavioral support alongside their prescription have better persistence and outcomes, which improves the return on every dollar of drug spend.
- Monitor utilization actively, not retroactively: Tracking who is on therapy, for how long, and with what outcomes catches early discontinuation and non-adherence before an employer pays for months of an unused prescription.
- Evaluate direct-to-consumer options where clinically appropriate: For some members, manufacturer pricing outside the plan can lower net cost without requiring broad formulary coverage.
Galileo builds the first two levers, clinical evaluation and lifestyle support, directly into how our care teams manage members.
Coverage-Only vs. Advanced Primary Care Approach to GLP-1s
Make GLP-1 Be Part of Advanced Primary Care
The coverage debate isn't going away, but it is the wrong place for employers to spend their strategic attention. Whether or not GLP-1s are on the formulary, the underlying question is the same: is weight being managed as an ongoing chronic condition, with a clinical team accountable for the outcome, or is it being treated as a one-time prescription decision made by a pharmacy benefit manager?
Galileo manages weight, metabolic health, and cardiovascular risk as connected parts of the same Advanced Primary Care model, with one clinical team responsible for candidacy, monitoring, and lifestyle support rather than three disconnected vendors.
If your GLP-1 spend is climbing faster than your results, talk to Galileo's employer team about what a comprehensive obesity management program could look like for your workforce.